Does a positive RPR or TPHA always mean active syphilis?
Not necessarily. Results must be interpreted together with symptoms, any previous treatment, and both treponemal and nontreponemal tests.
Syphilis is a treatable bacterial STI. It can cause a painless sore, a rash including the palms or soles, or no symptoms at all. Blood tests need careful interpretation.
Dr Neeraj Garg · MBBS (IMS-BHU), MD (IMS-BHU) · Dermatologist & STD / STI Specialist, Dehradun
Request an Appointment ↗For privacy, send only a simple appointment request through WhatsApp. Medical details can be discussed during consultation.
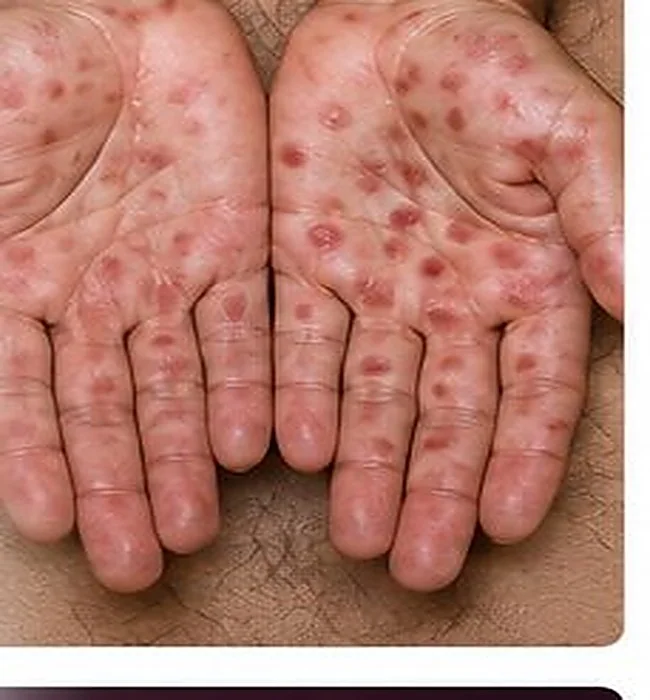
Educational illustration, not an actual clinical photograph. Signs vary and a diagnosis requires assessment.
The stage of infection and any previous treatment affect the meaning of a positive blood test and the appropriate treatment schedule.
Not necessarily. Results must be interpreted together with symptoms, any previous treatment, and both treponemal and nontreponemal tests.
RPR or VDRL titres help with diagnosis and follow-up; treponemal tests such as TPHA/TPPA help confirm infection and may stay positive after treatment.
Penicillin treatment depends on the stage of syphilis. A follow-up quantitative RPR may be needed to judge response, and pregnancy requires prompt medical attention.
Syphilis can cause no symptoms at some stages. A normal-looking examination cannot replace interpretation of the appropriate blood tests.
People commonly book an appointment for:
Assessment helps identify the likely cause, choose useful tests and explain treatment and follow-up without unnecessary medication.
Treponemal and quantitative nontreponemal serology (such as TPHA/TPPA and RPR); repeat testing if early infection is suspected. Examine for neurologic/ocular symptoms.
RPR or VDRL titres and a treponemal test such as TPHA/TPPA are interpreted together with symptoms and treatment history. Tests can be negative early after infection, so repeat assessment may be needed.
Common concerns explained in plain language. A test result or photograph alone may not tell the whole story.
A positive RPR or VDRL blood test needs interpretation alongside a treponemal test such as TPHA or TPPA, the quantitative titre, any past treatment and current symptoms. One result alone cannot determine whether infection is recent, previously treated or in need of therapy. Some false-positive results occur, so the full clinical picture matters.
TPHA and other treponemal tests often remain positive for years or life after adequate treatment. Follow-up usually relies on quantitative RPR or VDRL titres instead. Whether a change is significant depends on the size and persistence of the titre change, the stage of syphilis and any new exposure.
Primary syphilis may cause a painless ulcer, while secondary syphilis can cause a rash on the palms and soles. Not everyone has these classic signs. A suspicious sore or early exposure may need repeat testing even when an initial blood test is negative. Pregnancy or visual, hearing and neurological symptoms require prompt assessment.
Primary syphilis may present with a chancre, often painless. Secondary syphilis can cause rash (including palms and soles), mucosal lesions or systemic symptoms. Latent syphilis has positive serology without symptoms; early latent and late latent/unknown-duration infection are treated differently. Tertiary disease can involve cardiovascular or gummatous manifestations. Neurosyphilis, ocular syphilis and otosyphilis can occur at different stages.
RPR and VDRL are nontreponemal tests reported as titres; quantitative results help assess treatment response and possible reinfection. TPHA/TPPA are treponemal tests that help confirm infection and often remain reactive for life after treatment. Interpretation requires both types of tests, clinical history and previous results; a single positive test does not by itself establish disease activity.
During very early primary syphilis, blood tests may still be negative. If there is a suspicious ulcer or recent exposure, a negative initial RPR or treponemal test does not always exclude infection. A clinician may arrange direct lesion testing where available and repeat serology after an appropriate interval.
For uncomplicated primary, secondary or early latent syphilis, standard first-line treatment is benzathine penicillin G 2.4 million units intramuscularly once. For late latent syphilis or latent syphilis of unknown duration, the usual regimen is 2.4 million units intramuscularly weekly for three weeks. Neurosyphilis, ocular syphilis and otosyphilis require different specialist-directed intravenous treatment. Allergy, pregnancy and other circumstances change management; do not self-prescribe.
The same type of quantitative nontreponemal test, preferably from the same laboratory, should be used for follow-up. A fourfold titre change means two dilutions (for example 1:32 to 1:8, or 1:8 to 1:32). Expected decline and follow-up intervals vary with disease stage, HIV status, baseline titre and prior treatment; a titre alone should not trigger automatic retreatment.
Syphilis in pregnancy can cause miscarriage, stillbirth and congenital infection. Prompt antenatal testing, staging, penicillin treatment appropriate to the stage and partner assessment are essential. Penicillin is the only proven effective therapy for treating fetal infection and preventing congenital syphilis; pregnant patients with penicillin allergy generally need specialist-supervised desensitisation and penicillin.
After treatment of primary or secondary syphilis, quantitative nontreponemal titres are generally reviewed at 6 and 12 months; some patients need closer follow-up, including people with HIV. For latent syphilis, quantitative titres are generally reviewed at 6, 12 and 24 months. The expected response depends on stage, starting titre, prior treatment and clinical circumstances. A sustained fourfold rise, recurrent symptoms or an inadequate decline in context needs clinical reassessment, not automatic retreatment.
Within the first 24 hours after starting treatment for syphilis, some patients develop a short-lived reaction with fever, chills, headache, muscle aches or transient worsening of lesions. This is called the Jarisch–Herxheimer reaction and is not the same as penicillin allergy. It usually resolves within a day with supportive care. Pregnancy warrants special attention because the reaction can provoke contractions or fetal distress; urgent obstetric assessment is appropriate if concerning symptoms occur.
Penicillin-based treatment depends on stage and clinical circumstances. Quantitative RPR follow-up is important; partners require assessment. Pregnancy needs urgent specialist-guided management.
Penicillin treatment depends on the clinical stage. Follow-up usually includes quantitative RPR or VDRL titres and examination where indicated. Do not start injections or decide on the number of doses from a single positive result.
A focused, non-judgmental assessment is tailored to your symptoms and exposure history. An examination or test is recommended only when clinically appropriate, with your consent.
We understand that concerns about genital symptoms, sexual contact or a positive test can feel personal. Your appointment is approached respectfully, without blame or judgment.
Medical confidentiality is subject to applicable law and clinical obligations. Please avoid sending intimate photographs or detailed sexual histories in an appointment enquiry.
Dr Neeraj Garg holds MBBS (IMS-BHU) and MD (IMS-BHU) qualifications and provides dermatology and venereology consultations in Dehradun. The focus is on explaining symptoms, interpreting appropriate tests and discussing a practical next step.
Yes. This is possible during secondary syphilis, but other conditions may cause a similar rash.
Yes. Early syphilis may not yet produce detectable blood-test results. Repeat assessment may be needed after a recent exposure or suspicious sore.
RPR and VDRL are reported as titres and help follow treatment response. TPHA/TPPA are treponemal tests used to support diagnosis and may stay reactive after treatment.
No. Treponemal tests often remain positive for years or lifelong even after successful therapy.
No. The appropriate regimen depends on stage and circumstances. Some stages require one dose; late latent or unknown-duration infection usually requires three weekly doses.
It means a reduction by two dilutions, such as 1:32 to 1:8. Timing and interpretation depend on the clinical stage and previous results.
Yes. Some adequately treated patients remain serofast. A positive titre alone does not always mean active infection or treatment failure.
It can suggest reinfection or treatment failure and requires assessment of symptoms, exposures, previous treatment and repeat testing.
Follow-up often occurs at 6 and 12 months for primary or secondary syphilis and at 6, 12 and 24 months for latent syphilis, with individual adjustments.
Fever, chills or body aches may occur during the first day after starting syphilis treatment. It is not the same as penicillin allergy.
Yes. It can harm the fetus. Prompt antenatal evaluation and stage-appropriate penicillin treatment are essential.
New vision changes, eye pain, hearing loss or neurological symptoms in someone with possible syphilis need urgent medical assessment.
Symptoms overlap, and some infections cause no symptoms. These links help you find information, not diagnose yourself.
This patient guide is educational and does not replace an individual clinical assessment. Treatment and testing recommendations may change with local guidance, pregnancy, other conditions and antibiotic resistance.
Request a confidential STD / STI consultation with Dr Neeraj Garg, MBBS (IMS-BHU), MD (IMS-BHU), in Dehradun. Get individual guidance about symptoms, reports, testing and next steps.
Request an Appointment ↗Appointment enquiry only: there is no need to send intimate images or detailed medical information through WhatsApp.
Patient information updated 10 October 2026. This page provides general education and cannot replace an individual medical assessment. The appearance of a symptom does not by itself prove an STI.