Surgical removal
Complete excision with appropriate margins is the primary treatment for localized nail-unit melanoma. Options depend on depth, extent and tissue involvement.
Nail-unit melanoma is a rare but serious skin cancer that can arise in the nail matrix, bed or surrounding nail tissue. It may appear as a new or changing pigmented stripe, an irregular dark patch, nail damage, or sometimes a non-pigmented lump or sore. Early assessment and appropriate biopsy can be crucial.
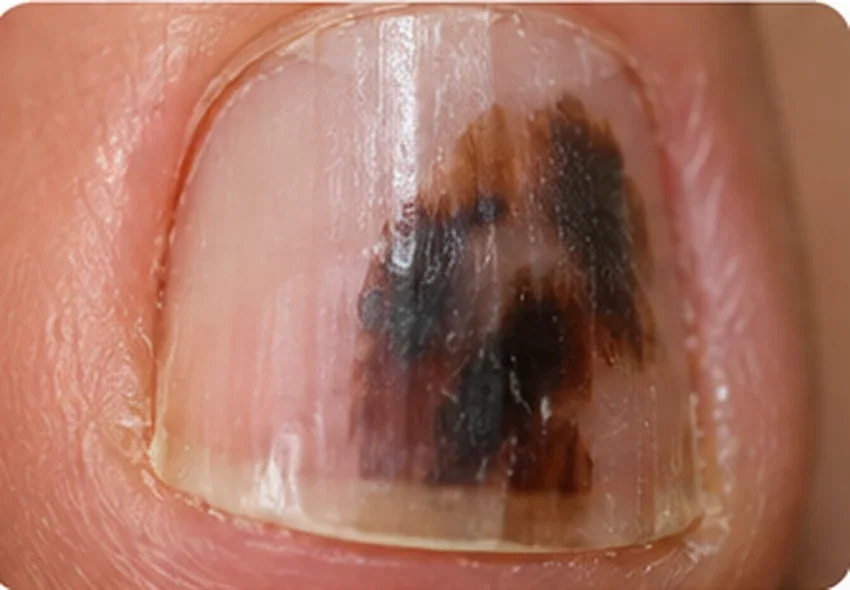
A new brown or black band, particularly if it is widening, uneven or has several shades.
Colour extending onto the cuticle or surrounding nail fold may be a warning sign.
New splitting, lifting, deformation or persistent loss of normal nail structure.
An ulcer, bump or sore beneath or around the nail that does not heal may be important even without dark pigment.
The ABCDEF guide helps people remember features that deserve examination. It does not diagnose melanoma or rule it out.
Seen more often in middle-aged and older adults, but it can occur at other ages.
A brown-black streak, particularly one with irregular colour, widening, or blurred edges. A narrow band may also require assessment.
A stripe that becomes wider or darker, or a nail lesion that does not improve despite appropriate treatment.
The thumb or big toe is often affected, but melanoma can develop in any fingernail or toenail.
Pigment spreading onto the nearby nail-fold skin (Hutchinson's sign) is a warning clue, although not diagnostic on its own.
A personal or family history of melanoma or atypical moles can add concern, but its absence does not rule out nail melanoma.
Important: These are warning clues, not a validated screening score. A small or pale lesion may still need assessment, and some nail melanomas have no dark pigment.
Nail-unit melanoma can develop in people of any age or skin tone, though it is more common later in adulthood. It often involves the thumbnail or big toenail, but any digit may be affected.
Most dark lines are not melanoma, but the cost of missing a suspicious nail lesion is high enough that prompt assessment is appropriate.
History of onset and change; assessment of nails and surrounding skin; check for concerning nail changes or a mass.
Magnified assessment of streak pattern, pigment asymmetry and nail-fold extension helps evaluate suspicion, but cannot reliably rule out melanoma on its own.
When examination raises concern, a nail-unit specialist selects a biopsy from the relevant nail matrix, nail bed or lesion, depending on its origin. When melanoma is suspected, a properly targeted nail-unit biopsy examined under the microscope (histopathology) is generally needed for a definitive diagnosis.
Further examination or investigations depend on tumour pathology and specialist guidelines. Not every patient needs the same imaging or lymph-node procedures.
The source of a pigmented band is often within the nail matrix, beneath the nail fold and plate. A superficial or wrongly placed sample may miss the abnormal tissue. The clinician must balance an adequate specimen for histopathology against the risk of permanently splitting, ridging or deforming the nail.
What happens next? If a nail lesion is clinically suspicious, timely assessment by an experienced nail-unit or melanoma specialist is recommended. Dermoscopy can guide evaluation, but it cannot replace histopathology when biopsy is indicated. Not every dark nail needs a biopsy.
Even a narrow new band can be suspicious if it progressively changes. Photographic monitoring alone is not a safe substitute for biopsy when a clinician suspects melanoma.
Complete excision with appropriate margins is the primary treatment for localized nail-unit melanoma. Options depend on depth, extent and tissue involvement.
Some early lesions may be treated with tissue-preserving surgery at experienced centres. More extensive disease can require larger surgery, and amputation may sometimes be necessary.
For selected invasive or advanced cases, melanoma specialists may consider sentinel node assessment and systemic treatments such as immunotherapy according to current guidelines.
Follow-up schedules are individualised based on tumour stage and treatments, and include attention to the surgical site and remaining skin/nails.
Clinic role: A dermatologist can recognise concerning nail changes, evaluate with dermoscopy and arrange prompt referral for specialist nail-unit biopsy when appropriate. Definitive melanoma surgery is performed by an appropriate specialist team, not advertised as a service at this clinic.
Early diagnosis is important, but the appearance of a dark band alone does not establish melanoma. Diagnosis requires professional examination and, when indicated, histopathology.
Treatment and investigation choices vary with the findings at examination. Do not start or stop medicines or attempt a nail procedure based on this page. The nail image is AI-generated for illustration and cannot identify a disease by itself.
Dr Neeraj Garg · MBBS (IMS-BHU), MD (IMS-BHU)
Maheshwari Hospital, Dalanwala, Dehradun · Consultation ₹800