Mild disease: treatment without surgery
Suitable early cases may improve with pressure relief, roomy footwear, correct nail trimming and clinician-guided taping or nail-edge support. Avoid digging at the corners or cutting beneath the skin yourself.
An ingrown toenail develops when the nail edge repeatedly presses into the surrounding skin, causing pain, swelling or drainage. Mild cases may improve with conservative care. For suitable persistent or recurrent cases, our clinic offers lateral (partial) or complete nail plate avulsion with chemical matricectomy, depending on the nail and its condition.
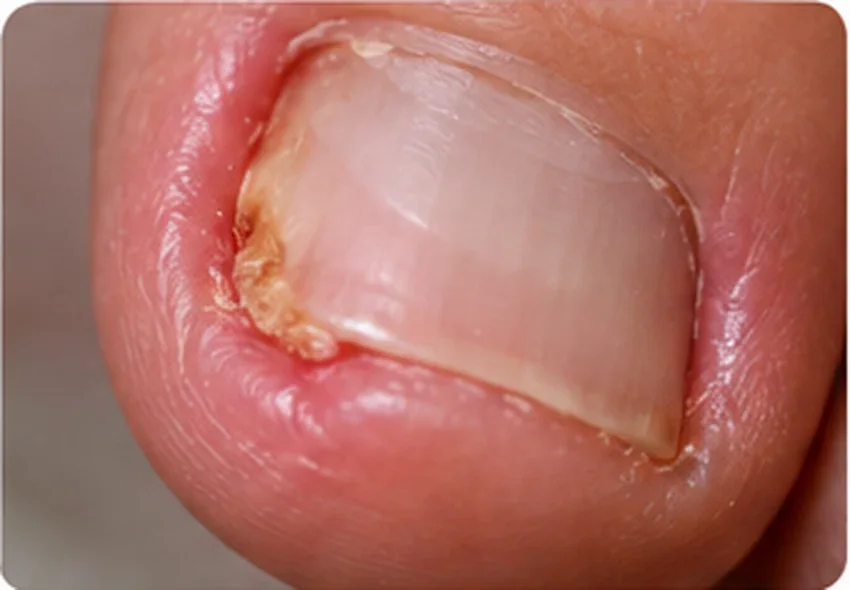
Local pain when pressing the side of the nail, slight redness or swelling.
Increasing nail-fold swelling, pain in shoes, granulation tissue or drainage.
Repeated tenderness or infection at the same corner despite trimming and home care.
Spreading redness, fever, a painful rapidly progressing infection or skin breakdown.
Local redness may be due to the body’s inflammatory reaction to the nail edge; it does not always indicate that antibiotics are necessary.
Incorrect trimming can worsen the problem. Digging beneath the nail with scissors or blades may introduce injury or infection.
The diagnosis is generally made by examining the involved nail, side fold and severity of swelling. Routine X-rays or cultures are not needed for most straightforward cases. Tests may be appropriate if there is severe infection, concern about deeper involvement, an atypical lesion or complicating medical conditions.
Mild discomfort versus recurrent painful swelling, granulation tissue or active cellulitis.
Diabetes, poor circulation, immunosuppression, anticoagulant use and any history of local anaesthetic allergy can affect treatment planning.
Relieve pain now, preserve as much nail as possible and reduce the chance of future ingrowing.
There is no single procedure for every ingrown toenail. The aim is to relieve pain, address the offending nail edge and reduce repeated ingrowing while preserving nail appearance when possible.
Suitable early cases may improve with pressure relief, roomy footwear, correct nail trimming and clinician-guided taping or nail-edge support. Avoid digging at the corners or cutting beneath the skin yourself.
The ingrowing side strip is removed after local anaesthesia. The corresponding lateral nail matrix (the nail-producing tissue) is treated with an appropriate chemical agent, helping prevent that troublesome edge from growing back. The remaining nail is generally preserved, although it becomes slightly narrower.
In selected nails with more extensive disease, deformity or other specific indications, the entire nail plate may be removed, with chemical treatment of the relevant matrix area as planned. The extent of matrix treatment determines how much nail can regrow. If the entire nail matrix is permanently destroyed, the nail will not grow back. This trade-off and cosmetic result are discussed before the procedure. Complete removal is not routinely necessary for a simple ingrown edge.
Redness at the ingrowing edge can be inflammatory rather than a spreading bacterial infection. Oral antibiotics are not routinely needed after uncomplicated nail surgery, but may be prescribed for spreading cellulitis or another significant infection.
Nail avulsion removes the nail plate, which normally grows again if the matrix remains intact. Chemical matricectomy treats the nail-producing matrix to stop the selected portion of nail from regrowing. Treating the matrix is the key step that helps prevent recurrence in suitable cases.
These estimates come from different published studies, not a direct comparison or an audited recurrence rate from our clinic. The approximately 5% figure mainly reflects lateral chemical matricectomy (particularly phenol techniques) and does not apply automatically to every chemical agent or complete-avulsion procedure. Neither treatment guarantees a particular outcome; nail regrowth after simple avulsion is not the same as recurrence of an ingrown toenail.
The exact steps and whether lateral or complete avulsion is appropriate are decided after examining the nail.
Assess the affected nail, degree of inflammation and whether a partial or complete avulsion is appropriate.
A local anaesthetic injection is given. Pressure or handling may be felt, but sharp procedural pain should be controlled.
Remove the ingrowing lateral strip or the full plate, depending on the agreed plan.
Apply a chemical agent to the chosen nail-producing matrix area to reduce unwanted nail regrowth. The extent of treatment affects the eventual nail shape.
Apply a suitable dressing, discuss expected drainage and discomfort, and give personalised wound-care and review instructions.
Most patients can walk carefully soon after the procedure, but recovery is individual. Healing can take longer after complete avulsion, extensive tissue inflammation or chemical matrix treatment.
Keep the initial dressing as instructed, elevate the foot when possible and use prescribed pain relief. Avoid running or pressure on the toe.
The initial dressing is often checked or changed within this period, according to your surgeon's specific protocol. Gentle walking is usually possible as tolerated.
Use roomy footwear and follow the cleaning and dressing plan. Some tenderness and clear or lightly blood-stained fluid may be expected.
Many wounds heal in roughly 2–4 weeks, but drainage or delayed healing can last longer, particularly after chemical matricectomy or complete avulsion.
These are general recovery estimates, not a substitute for your individual postoperative plan. People with diabetes, reduced sensation, poor circulation or other medical risks require tailored follow-up.
Treatment and investigation choices vary with the findings at examination. Do not start or stop medicines or attempt a nail procedure based on this page. The nail image is AI-generated for illustration and cannot identify a disease by itself.
Dr Neeraj Garg · MBBS (IMS-BHU), MD (IMS-BHU)
Maheshwari Hospital, Dalanwala, Dehradun · Consultation ₹800