Non-segmental vitiligo
The more common form. Patches may occur on both sides of the body and can change over time, sometimes involving the hands, face or trunk.
White patches may be vitiligo — but not every pale patch is. Get an individualised assessment of the diagnosis, extent and activity, with evidence-based options to help control spread and support repigmentation.
Consultation ₹800 · Maheshwari Hospital, Dalanwala, Dehradun
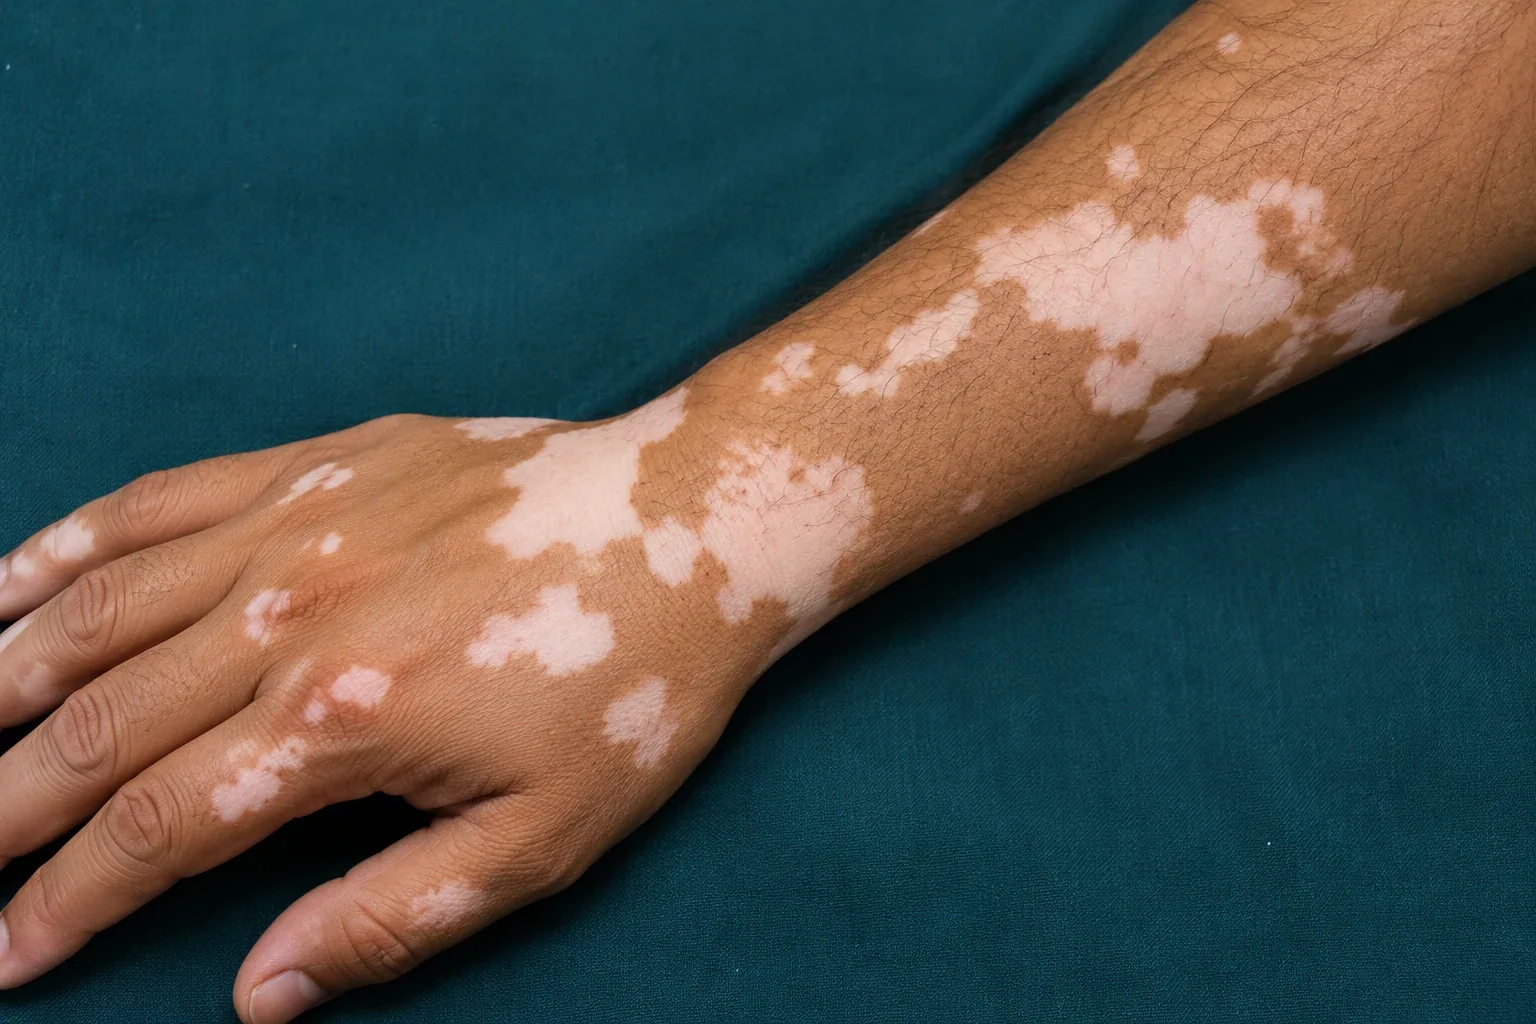 Personalised vitiligo care
AI-generated illustration for education, not a patient photograph.
MBBS (IMS-BHU), MD (IMS-BHU)
Dermatologist & Venereologist · Dehradun
Dr Neeraj Garg completed both MBBS and MD at the Institute of Medical Sciences, Banaras Hindu University (IMS-BHU). He provides evidence-based assessment for skin, hair, nail and sexually transmitted conditions, with individualised care, clear counselling and patient privacy.
 MBBS + MDBoth from IMS-BHU
Vitiligo causes loss of skin pigment, producing well-defined pale or white patches. The size, shape and location vary. The examples below are AI-generated educational illustrations, not clinical photographs.
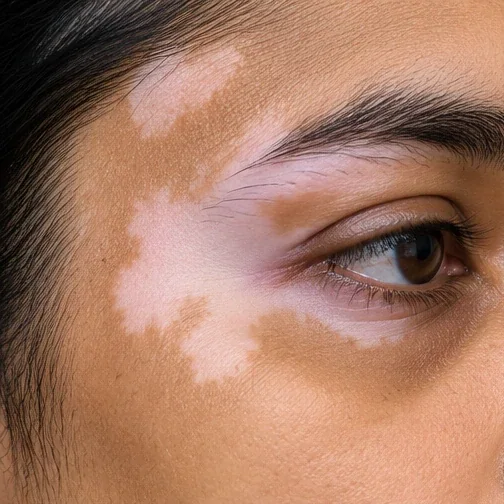
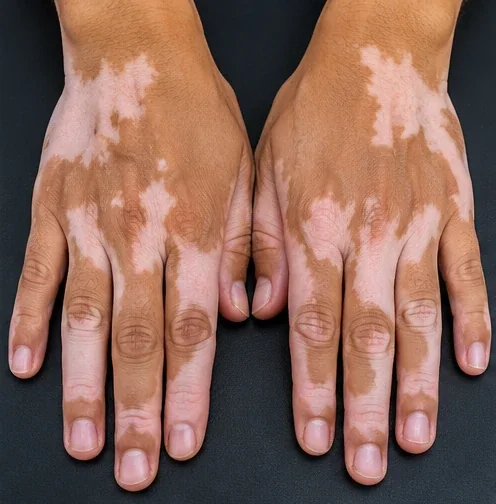
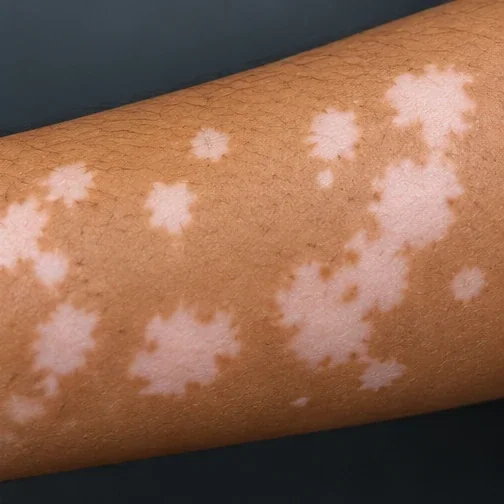
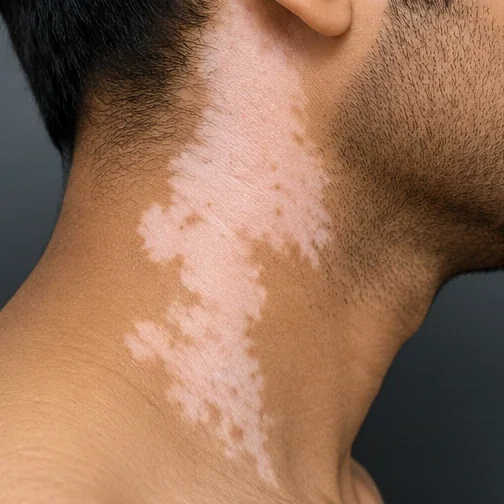
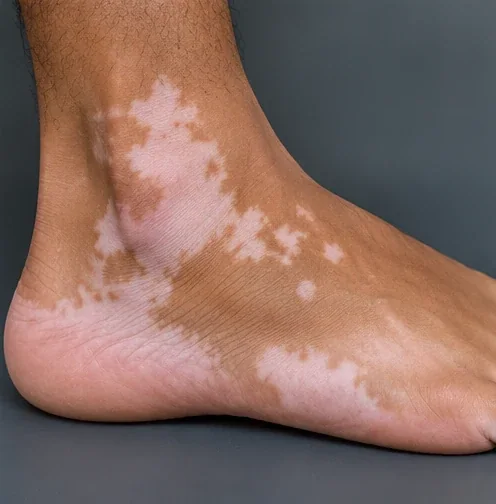
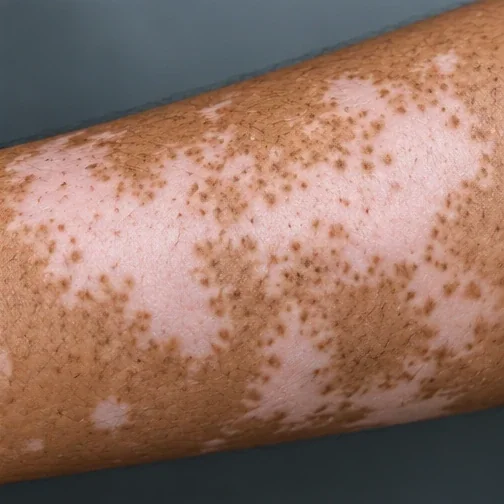
Vitiligo occurs when pigment-producing cells called melanocytes are damaged or lost. It is usually an immune-mediated condition in which the immune system mistakenly targets these cells.
Vitiligo is commonly linked to immune-mediated loss of melanocytes. Some people with vitiligo also have other autoimmune conditions, particularly autoimmune thyroid disease.
Inherited susceptibility can increase the likelihood of developing vitiligo, but most patients do not have a close relative with the condition.
Skin injury, friction, repeated rubbing, sunburn or certain chemical exposures may contribute to the appearance of patches in susceptible individuals. These factors do not explain every case.
Vitiligo is not contagious. It is not caused by poor hygiene, normal contact with other people, or ordinary food combinations.
Clinical assessment is particularly useful if patches are new, enlarging or affecting visible or sensitive areas.
Recent appearance of several new white areas, expanding borders or rapid change may indicate active disease.
Eyebrows, eyelashes, scalp hairs or fingertip involvement may influence counselling and treatment choice.
Visible colour change can affect confidence and daily life. Getting a clear explanation and options may help.
The goal is to confirm the diagnosis, assess whether it is active or stable, and discuss practical treatment choices.
Review onset, distribution, progression, family history, prior creams and potential triggers or injuries.
Examine the skin and use Wood’s lamp when helpful. Record affected areas and any signs of activity.
Consider site-specific topical therapy, phototherapy when appropriate and options for stable disease.
Monitor for spread and repigmentation, check tolerability and adapt the long-term plan.
Most cases are diagnosed clinically. A dermatologist also checks the pattern, affected sites and whether patches are changing.
Examination and Wood’s lamp. A specialised UV examination can make depigmented skin more apparent, helping distinguish vitiligo from some mimicking conditions.
Look for disease activity. Recent expansion, new lesions and other clinical features guide treatment goals. Serial photographs may help monitor progress.
Tests only when indicated. A biopsy is rarely necessary. Thyroid history and, where appropriate, thyroid tests may be considered because vitiligo can coexist with autoimmune thyroid disease.
There is no single treatment that reliably restores pigment in every patient. The plan is tailored to distribution, activity, age, prior response and preferences.
Appropriately selected corticosteroids and topical calcineurin inhibitors such as tacrolimus may help selected areas. The face and skin folds need particular care in choosing medicines and duration.
NB-UVB is an established option for more extensive, progressive or treatment-resistant vitiligo. A supervised course often requires repeated sessions over several months. Suitability and access are discussed individually.
When patches are rapidly spreading, controlling disease activity can be a priority. Selected patients may need a specialist-supervised short course of systemic treatment; this is not routinely required for everyone.
Specialist grafting techniques may be considered for selected, sufficiently stable lesions. Targeted light treatment is a separate option for suitable localised patches and does not necessarily require disease stability. Availability should be confirmed before planning a procedure.
No treatment guarantees permanent pigment restoration. Many patients achieve worthwhile repigmentation, but response and the chance of recurrence vary. Periodic follow-up helps guide realistic long-term care.
Skin site, the age and activity of lesions and whether pigment-producing hair follicles remain can affect the likelihood of repigmentation.
Often respond more favourably to topical treatment or phototherapy than hands and feet, although results differ.
These can be slower and more resistant to repigmentation. Early assessment can help set appropriate goals.
Loss of hair pigment can make repigmentation harder in that area. Treatment decisions still depend on the overall assessment.
Daily care helps protect depigmented skin and prevent avoidable irritation, but it cannot replace medical treatment where indicated.
Depigmented skin can burn more easily. Use suitable sun protection, including broad-spectrum SPF 50 sunscreen, shade and protective clothing.
Repeated friction, scratching or cuts can sometimes trigger new areas in susceptible patients (Koebner phenomenon).
Do not use bleaching chemicals, irritating oils or unsupervised medications to try to “restore colour”.
No diet has been proven to cure vitiligo. Avoid unnecessary food restrictions unless medically indicated.
Skin camouflage is a reasonable optional choice for people who prefer temporary colour matching.
Appearance changes may affect confidence or mood. Patient preferences and emotional wellbeing should be part of care.
No. Vitiligo is not an infection and cannot spread by touch, shared towels, food or ordinary contact.
No. Conditions such as pityriasis alba, fungal infection and post-inflammatory hypopigmentation may look similar. Examination and sometimes Wood’s lamp evaluation can help.
Yes. Some patients develop new patches over time, while others remain stable for long periods. Activity varies by person and vitiligo type.
There is no guaranteed permanent cure. Treatments can help stabilise disease or restore pigment in selected patches, and results vary.
No. Facial patches generally tend to repigment better than fingers and feet. Individual results also depend on other clinical factors.
It is an examination using long-wave ultraviolet light that can highlight areas of pigment loss and help assess some white-patch disorders.
Not necessarily. Testing is guided by medical history, examination and possible associated conditions. Some patients may benefit from evaluation for thyroid problems.
Treatment is adapted to the child’s age, sites involved and the effect on everyday life. Extra care is taken with potent topical steroids and phototherapy decisions.
Facial skin needs particular caution because inappropriate or prolonged topical steroid use can cause adverse effects. Nonsteroidal alternatives may be preferred for some facial sites.
No. NB-UVB may be useful for selected patients, but age, extent of disease, travel commitments and treatment safety must be considered.
Specialist grafting procedures can be considered for carefully selected, stable vitiligo when other treatments have not helped. They are usually not appropriate when disease is actively spreading.
Vitiligo has an immune-related basis. Stress may be relevant to disease experience and triggers in some people, but blaming stress alone is not an accurate explanation.
Dr Neeraj Garg · MBBS (IMS-BHU), MD (IMS-BHU) · Maheshwari Hospital, Dalanwala, Dehradun. Consultation ₹800 · Please book your appointment.
Medical content is educational and does not replace examination or individual prescriptions. AI-generated imagery is illustrative.