Round patches
Smooth, well-demarcated areas without obvious scarring.
Alopecia areata is an immune-mediated condition in which inflammation disrupts normal hair growth, often causing sharply defined bald patches on the scalp, beard, eyebrows or other hair-bearing sites. It is not contagious, and regrowth is possible, though relapses can occur.
Consultation ₹800 · Pre-booking required · No advance booking payment
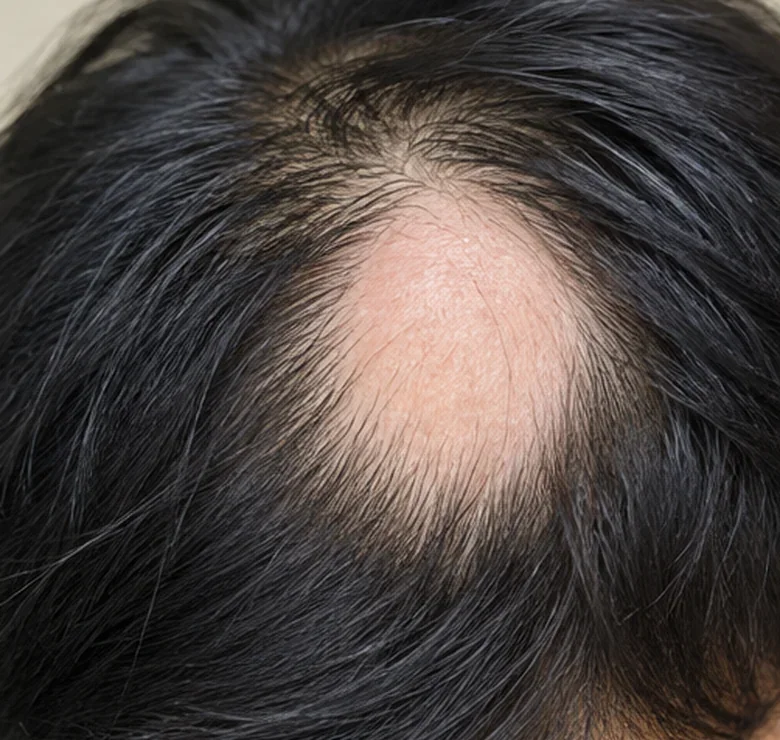
These clues help distinguish one kind of hair loss from another—but images and symptoms alone cannot confirm a diagnosis.
Smooth, well-demarcated areas without obvious scarring.
A patch can become noticeable over days or weeks.
Beard, eyebrows, eyelashes or nails may also be involved.
Some patches regrow; others enlarge or recur.
In alopecia areata, immune inflammation interrupts hair growth without usually destroying the follicles. That is why regrowth remains possible even when the scalp looks completely smooth.
Some patients have one or two small patches. Others develop more extensive scalp or body hair loss. Nails may develop small pits or other changes. Its course is unpredictable: spontaneous regrowth can occur, but recurring episodes are also common.
Clinical history and scalp examination guide whether trichoscopy, laboratory tests, microscopy or biopsy is needed. Not every patient requires all investigations.
Check shape and distribution of patches, eyebrow/beard involvement and nail changes.
Look for characteristic short broken hairs, exclamation-mark hairs and yellow or black dots, while distinguishing fungal infection and hair pulling.
Most typical cases can be diagnosed clinically. Thyroid assessment or other tests are considered when clinically indicated; routine broad autoimmune testing is not needed for everyone.
Alopecia areata does not always appear in the same way. Recognising the pattern helps patients understand why severity, prognosis and treatment choices can differ.
The commonest form. One or more smooth, well-defined bald patches appear on the scalp, beard or other hair-bearing sites.
Alopecia totalis means complete scalp-hair loss. Alopecia universalis means complete loss of scalp, facial and body hair.
Some patients develop band-like loss along the sides and back of the scalp, called ophiasis. Pattern and extent can influence treatment planning and prognosis.
Management depends on the actual condition, its severity, age, medical history and your goals. Procedures are not a replacement for treating the underlying cause.
Observation can be reasonable for selected small, recent patches. Topical corticosteroids or intralesional corticosteroid injections may be considered according to age, site and severity. Injections are most often used for a limited number of patches in suitable adults; they are not the right choice for everyone.
Widespread disease may need specialist systemic therapy, sometimes including JAK inhibitors where approved, accessible and suitable. These treatments require careful screening, safety counselling and monitoring.
Minoxidil may sometimes be used as an adjunct, but it does not replace treatment directed at the underlying immune process. With widespread or rapidly progressing disease, treatment choices need individual assessment.
Follow-up matters because new patches or recurrence can develop even after apparent regrowth. Discuss expectations, psychological impact and alternative approaches where appropriate.
Hair grows slowly. These are broad clinical milestones, not a guaranteed timetable for recovery or response.
Confirm non-scarring alopecia and grade the extent of loss.
Observe for new patches and signs of regrowth; treatments need time.
Regrowth and recurrence are both possible; management is individualised.
Clear answers without unrealistic promises or one-size-fits-all treatments.
Do not begin or discontinue prescription treatments solely from a webpage. A dermatologist can identify overlapping disorders and discuss benefits, contraindications and follow-up. All clinical images on this page are AI-generated illustrations—not photographs of patients or treatment results.
Dr Neeraj Garg · MBBS (IMS-BHU), MD (IMS-BHU)
Maheshwari Hospital, Dalanwala, Dehradun · Consultation ₹800